Three studies presented Saturday at the American Heart Association’s scientific sessions examined how far clinicians should go to lower blood pressure in people with especially difficult risk profiles: those recovering from stroke and those living with type 2 diabetes.
Taken together, the results supported a more aggressive stance after stroke but not a blanket move to lower targets in diabetes. That split matters because hypertension is a major driver of recurrent cardiovascular events in both groups, yet the evidence in the new reports did not point to one strategy that fits all high-risk patients.
Jordana Cohen of the Perelman School of Medicine at the University of Pennsylvania said blood pressure is defined in guidelines as the most important modifiable risk factor for recurrent stroke and that blood pressure control after stroke is suboptimal. Bruce Ovbiagele of the UCSF Weill Institute for Neurosciences added that one-third of stroke patients do not meet blood pressure guidelines and that about one out of five stroke survivors have discontinued their antihypertensive medications one year after a stroke.
The data
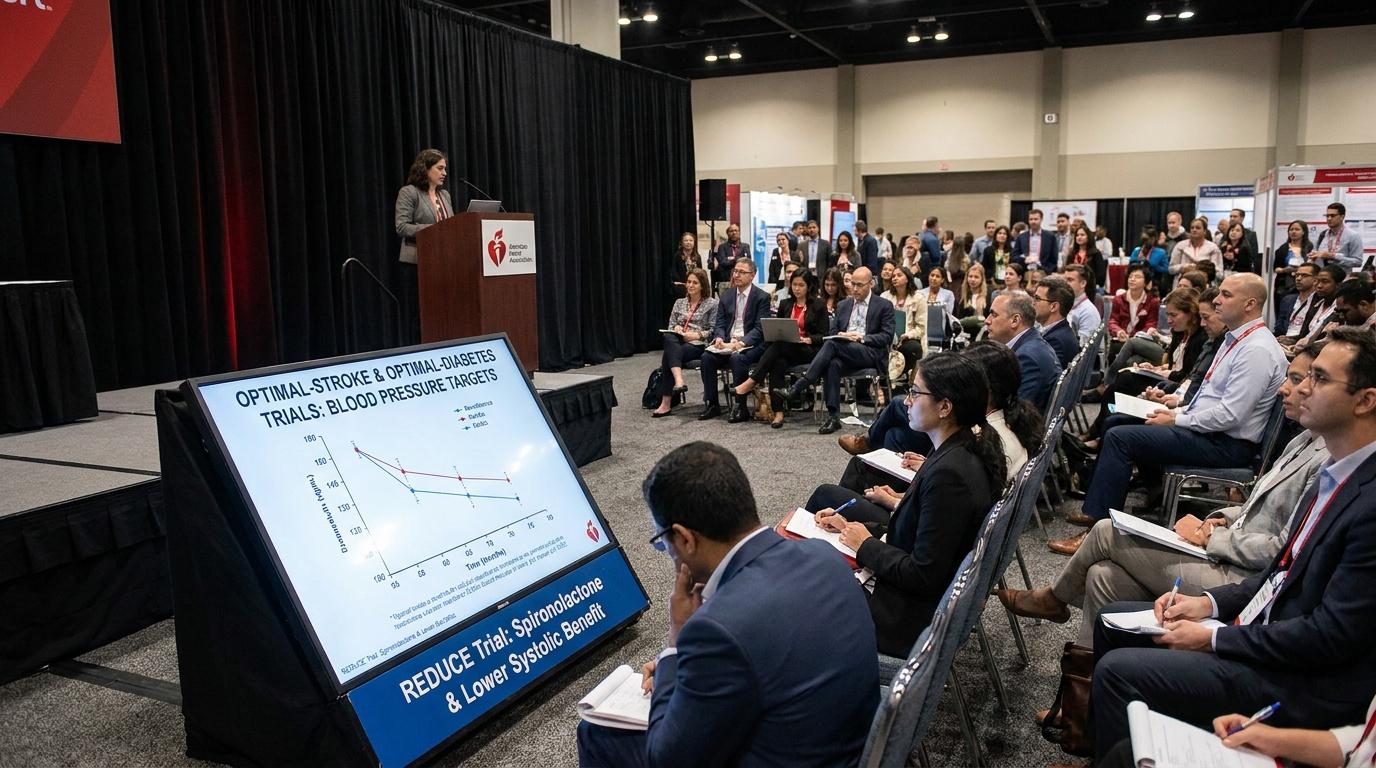
Cohen’s REDUCE trial tested spironolactone, a common and inexpensive diuretic that is often used only after three other medications have not worked. In this small but diverse study, giving spironolactone soon after a stroke made patients more likely than those receiving usual post-stroke care to reduce blood pressure to less than 130/80 mm Hg three months later.
Cohen said the trial was designed to measure blood pressure reduction rather than cardiovascular outcomes. She also said that even small changes can matter, noting that a drop of as little as 7 mm has been associated with a 38% lower risk of recurrent stroke. The REDUCE trial was presented as an abstract and has not yet been published in a medical journal.
A separate and much larger study from Brazil, OPTIMAL-STROKE, asked a different question: whether aiming for a systolic blood pressure of 120 mm Hg or lower would outperform the currently recommended 140 mm Hg target after stroke. Gisele Sampaio of the Federal University of Sao Paulo in Brazil said that almost all patients enter stroke-based antihypertensive therapy, but the unanswered issue is how low clinicians should go.
According to the study, which was published in the New England Journal of Medicine, patients treated to the lower systolic goal were significantly less likely to die or have cardiovascular events within four years than those treated to below 140 mm Hg. The nonfatal events counted in OPTIMAL-STROKE included heart attack, stroke, and hospitalization for chest pain or heart failure.
The safety picture in OPTIMAL-STROKE was not without tradeoffs. Otavio Berwanger of Imperial College London and chair of the OPTIMAL study steering committee said reaching the lower target requires medical supervision, including monitoring kidney function. He said there was no increase in end-stage renal disease, no increase in the need for dialysis, and no increase in deaths, but some renal markers were abnormal. He also said there were changes in electrolyte levels consistent with diuretic use or with how much water people drink.
The related OPTIMAL-DIABETES trial, also published in the New England Journal of Medicine, did not show the same advantage for pushing lower. Karla Santo of Einstein Hospital Israelita in Sao Paulo said the ideal blood pressure target in patients with type 2 diabetes remains uncertain. In that study, aiming for a systolic blood pressure of less than 120 mm Hg rather than less than 140 mm Hg did not reduce major cardiovascular events or deaths.
Why the split matters
The practical signal from the three studies is that intensive blood pressure control may depend heavily on clinical context rather than on the assumption that lower is always better across populations with elevated cardiovascular risk.
Shawna Nesbitt of UT Southwestern Medical Center said differences between men and women and between younger and older patients in earlier studies and in OPTIMAL-DIABETES suggest a more nuanced approach may be needed. She said the diabetes trial supports rather than rebukes earlier evidence for more aggressive treatment in some patients with diabetes, while raising the possibility that patient groups have been lumped together in ways that are not always advantageous.
That is a meaningful distinction for practice. Post-stroke care may justify earlier or more intensive antihypertensive treatment, but diabetes alone did not produce a clear benefit from the lower target in this new study. For systems trying to standardize care pathways, the data argue against turning one favorable post-stroke result into a universal intensive-treatment rule.
The implementation problem
The sources also pointed to a delivery challenge that sits outside the trial designs themselves. Ovbiagele said post-stroke care is very fragmented, with neurologists treating patients in hospital before primary care takes over later, raising the question of how a nephrologist, neurologist, and primary care clinician should manage the use of these medications together.
Cheryl Bushnell of Wake Forest University said the issue is not knowing what to do but how to do it. That operational point may be the most immediate implication of the meeting presentations: the evidence for tighter blood pressure control after stroke is getting stronger, but the ability to carry it out safely depends on sustained follow-up, medication persistence, and cross-specialty management that many care pathways still do not handle well.